

Fertility

Fertility

Fertility preservation

Fertility Preservation

Fertility Preservation

Keeping More Options Open for Your Future

Life plans do not always align with the biological timeline for having children. Fertility changes with age and health. In women, both the number and quality of eggs decline with age. Male fertility may also be affected by aging, illness, medical treatment, and lifestyle factors.

A professional fertility assessment can help you understand your current reproductive health. Fertility preservation may offer additional options for the future while reproductive potential remains. Whether you are not yet planning to have children, are preparing for treatment that may affect fertility, or would like to plan ahead, our reproductive medicine team can help you explore suitable options.


What Is Fertility Preservation?

Fertility preservation involves freezing eggs, sperm, embryos, or reproductive tissue before reproductive function may decline because of age, illness, or treatment. These may later be used with an appropriate assisted reproductive treatment, depending on individual circumstances.

Common Assessment and Preservation Options

  • Female fertility assessment
  • Male fertility assessment
  • Egg freezing
  • Sperm freezing
  • Embryo or reproductive tissue preservation for specific medical indications

Fertility preservation does not guarantee a future pregnancy. It offers a possible option based on your reproductive health at the time of preservation. Egg freezing outcomes are influenced by age at freezing, the number of mature eggs stored, and individual health factors.

Who May Consider Fertility Preservation?

  1. People who are not planning to have children soon: If you are focusing on education, career development, financial planning, or have not yet met a suitable partner, a fertility assessment can help you understand your current reproductive health and explore future options.
  2. People preparing for medical treatment: Certain illnesses and treatments, including chemotherapy, radiation therapy, and some operations, may affect the ovaries, testes, or reproductive cells. When the treatment schedule allows, consult a fertility specialist before treatment begins so that your primary medical team and reproductive medicine team can coordinate care.
  3. People at risk of declining reproductive function: If you have diminished ovarian reserve, a history of ovarian surgery, endometriosis, or a family history of early menopause, discuss whether an earlier fertility assessment and planning would be appropriate.
  4. Men who wish to preserve reproductive options: Sperm freezing may be considered before treatment or surgery that could affect sperm production, when sperm count or motility is reduced, or when providing a semen sample in the future may be difficult.

What Does a Fertility Assessment Include?

A fertility assessment involves more than a single test result. Your doctor considers age, medical history, menstrual patterns, ultrasound findings, blood tests, and reproductive goals together.


Common Female Fertility Assessments

  1. Anti-Müllerian hormone (AMH): AMH helps estimate ovarian reserve and predict how the ovaries may respond to ovarian stimulation.
  2. Transvaginal ultrasound and antral follicle count (AFC): Ultrasound is used to count small follicles in the ovaries and assess the uterus, ovaries, and pelvic structures.
  3. Hormone testing: Depending on your needs, testing may include FSH, LH, estradiol (E2), thyroid function, or prolactin.

AMH and AFC mainly reflect egg quantity and the likely response to stimulation. They do not independently measure egg quality or directly predict whether natural pregnancy will occur. Age remains an important factor in assessing reproductive outcomes.


Common Male Fertility Assessments

  • Assessment usually includes a reproductive and medical history and semen analysis to evaluate semen volume, sperm concentration, motility, and morphology. If results are abnormal, your doctor may recommend hormone tests, ultrasound, chromosome testing, or other investigations.
  • When a couple is planning pregnancy or has been trying to conceive without success, both partners should be assessed rather than focusing on only one partner.


What Is Egg Freezing?

Egg freezing involves retrieving eggs from the ovaries and preserving them using cryopreservation. When you wish to use them in the future, the eggs are warmed, fertilized, and cultured into embryos. Embryo transfer is then planned according to your health and treatment needs.

The Egg Freezing Process

1. Consultation and Fertility Assessment

Your doctor reviews your age, menstrual cycle, medical history, reproductive goals, and medications, and arranges AMH testing, ultrasound, and other relevant assessments.

2. Ovarian Stimulation and Follicle Monitoring

Medication is prescribed according to your ovarian reserve. Follow-up blood tests and ultrasound scans are needed to monitor follicle growth.

3. Egg Retrieval

Egg retrieval is scheduled when the follicles are ready. The procedure is usually performed under anesthesia or sedation, after which the embryology laboratory assesses the number of mature eggs.

4. Egg Cryopreservation

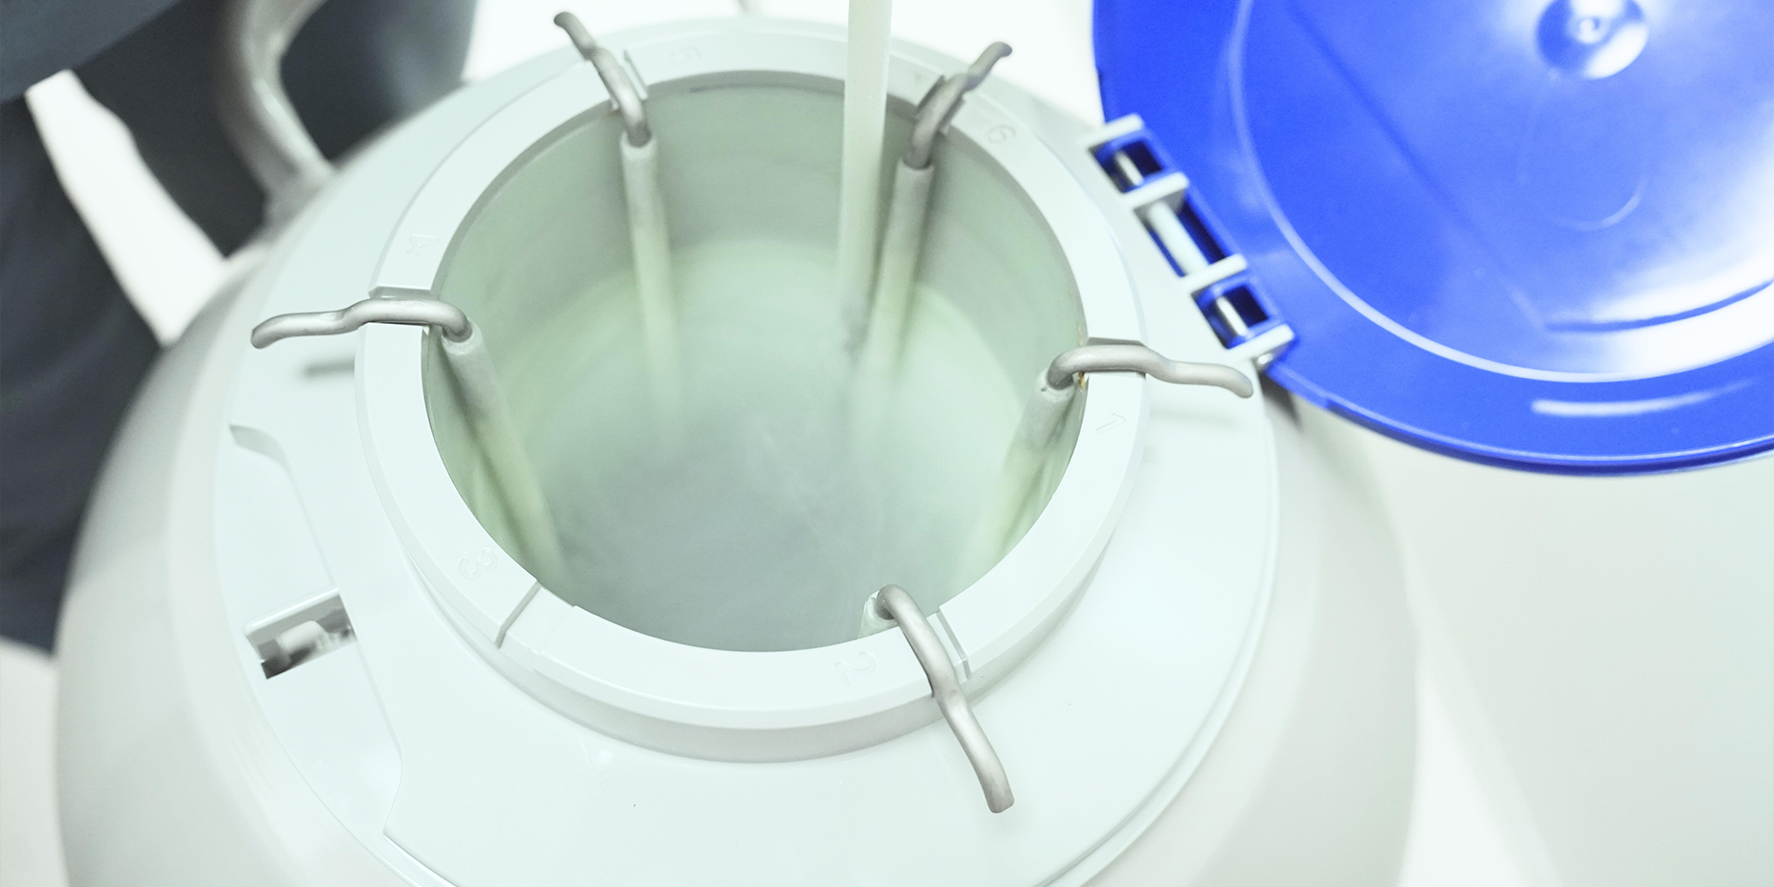
Suitable mature eggs are prepared and preserved using vitrification, a rapid-freezing technique, and stored in liquid nitrogen storage systems.

5. Future Use

When needed, the eggs are warmed and used for fertilization, embryo culture, and subsequent embryo transfer as part of a treatment plan.

An egg freezing cycle generally takes about two to three weeks. The actual schedule varies with your menstrual cycle, medication protocol, and ovarian response.

Does Egg Freezing Guarantee a Future Pregnancy?

No. Egg freezing preserves eggs at the age at which they were retrieved, but it cannot guarantee a future pregnancy.

The eggs must still survive warming, fertilize, develop into embryos, and implant. Each stage may be affected by age, egg number and quality, sperm factors, and the uterine environment.

Egg freezing preserves the age of the eggs, but it does not stop the body from aging. Risks such as gestational hypertension, gestational diabetes, and other age-related pregnancy complications remain associated with your age and health at the time of pregnancy. Egg freezing should therefore not be viewed as a way to postpone parenthood indefinitely. Continue discussing your reproductive plans with your doctor after storage.


What Are the Possible Risks of Egg Freezing?

Most patients recover well after ovarian stimulation and egg retrieval. Possible symptoms include bloating, injection-site discomfort, mood changes, and pelvic discomfort.

A small proportion of patients may develop ovarian hyperstimulation syndrome (OHSS), which can cause significant bloating, nausea, breathing discomfort, reduced urine output, or rapid weight gain. Your doctor adjusts the treatment according to AMH, AFC, and your response to medication to help reduce these risks.

What Is Sperm Freezing?

Sperm freezing involves analyzing and processing a semen sample, dividing it into storage units, and cryopreserving it. Depending on sperm count and motility after thawing and the partner’s reproductive health, the sperm may later be used for intrauterine insemination (IUI), in vitro fertilization (IVF), or intracytoplasmic sperm injection (ICSI).

The Sperm Freezing Process

1. Medical consultation and relevant infectious disease screening.

2. Semen collection according to the medical team’s instructions.

3. Semen analysis and sample processing.

4. Addition of cryoprotectant and division into storage units.

5. Thawing of the required units when needed for treatment.

Samples are usually divided into several storage units so that they do not all need to be thawed at once. However, not all sperm survive freezing and thawing. Your doctor will recommend the number of collections and storage units according to the results.

Frequently Asked Questions

Does a low AMH level mean I cannot get pregnant?

Not necessarily. AMH mainly reflects ovarian reserve and the likely number of eggs obtained during ovarian stimulation. It cannot independently determine egg quality or the chance of natural pregnancy. Age, menstrual patterns, ultrasound findings, and other assessments must also be considered.

Is one egg freezing cycle enough?

Not always. The number of mature eggs to store depends on age, ovarian reserve, response to treatment, and the number of children you hope to have. After the first retrieval, your doctor can discuss whether another cycle would be appropriate.

Should I have a fertility assessment even if I am young?

It depends on your medical history, reproductive goals, and risk factors. If you are concerned about your ovarian reserve or planning to delay pregnancy, discuss whether an assessment would be useful with your doctor.

Can men also benefit from fertility preservation?

Yes. Male fertility may be affected by illness, medical treatment, surgery, age, and lifestyle factors. Discuss sperm freezing and future reproductive plans early, particularly before treatment that may damage sperm production.

Fertility Preservation Begins with Understanding Your Options

Fertility preservation is not about pressuring everyone to have children immediately or suggesting that everyone needs to freeze eggs or sperm. It is about making informed choices based on age, health, and future plans.

The Reproductive Medicine Center at Sung Jun Hung Women’s and Children’s Hospital provides fertility assessments, egg freezing, sperm freezing, and personalized reproductive planning. If you are not yet ready for pregnancy, are concerned about declining fertility, or are preparing for treatment that may affect reproductive function, consider arranging an early consultation.
Egg freezing

Egg Freezing

Your Guide to Egg Freezing

The Process, Who May Benefit, Risks, and Aftercare

Not being ready for pregnancy now does not mean you do not want children in the future. Work commitments, family plans, relationships, or medical treatment may not align with your preferred timing for parenthood. Egg freezing is one fertility preservation option that involves retrieving and storing mature eggs for possible future use.

However, egg freezing does not guarantee a future pregnancy. Outcomes depend on age at freezing, ovarian reserve, the number of mature eggs stored, sperm factors, embryo development, and health at the time of pregnancy. A comprehensive assessment by a fertility specialist is therefore important before treatment.

What Is Egg Freezing?

Egg freezing, also called oocyte cryopreservation, begins with ovarian stimulation to help several follicles grow within one treatment cycle. Eggs are then collected through an egg retrieval procedure. The embryology laboratory assesses their maturity, and suitable mature eggs are preserved by vitrification and stored in liquid nitrogen storage systems.

When you wish to use the eggs, they are warmed and usually fertilized using intracytoplasmic sperm injection (ICSI). The fertilized eggs are cultured into embryos, and embryo transfer is planned according to your uterine condition and overall health.

Who May Consider Egg Freezing?

  1. Women who are not planning pregnancy soon: If you are prioritizing work, education, finances, or other life plans, or have not yet met a suitable partner, a fertility assessment can help you discuss whether egg freezing is appropriate.
  2. Women preparing for treatment that may affect fertility: Certain chemotherapy, radiation therapy, hormonal treatments, and pelvic or ovarian operations may affect ovarian function. If your condition and treatment schedule allow, seek an early referral to discuss egg freezing, embryo freezing, or other preservation options.
  3. Women at risk of diminished ovarian reserve: A history of ovarian surgery, endometriosis, ovarian tumors, or early menopause in the family may warrant earlier assessment and planning.
  4. People considering preservation before medical or gender-affirming treatment: Some hormonal and surgical treatments may affect reproductive function. Discuss options with both your primary treatment team and a fertility specialist before treatment begins.

Is Earlier Egg Freezing Always Better?

Age at egg retrieval is an important factor in treatment outcomes. Egg number and quality decline with age, while the likelihood of embryo chromosome abnormalities and miscarriage increases. Freezing eggs while ovarian reserve remains favorable may offer a better opportunity to collect an adequate number of mature eggs.

This does not mean every young woman needs to freeze eggs immediately. The decision should consider near-term pregnancy plans, age, AMH, AFC, medical history, desired family size, and practical factors such as time and cost.

What Assessments Are Needed Before Egg Freezing?

1. Medical History and Reproductive Planning

Your doctor reviews menstrual patterns, pregnancy and surgical history, gynecological conditions, family history of early menopause, current medications, and your preferred timing and family size. If treatment for cancer or another illness is planned, the teams also coordinate the treatment type, start date, and suitability for ovarian stimulation.

2. AMH Blood Test

AMH helps assess ovarian reserve and predict the likely response to stimulation and egg yield. It mainly reflects egg quantity rather than quality and cannot independently predict natural pregnancy or guarantee a particular number of mature eggs.

3. Transvaginal Ultrasound and AFC

Ultrasound is used to count antral follicles in both ovaries and look for ovarian cysts, uterine fibroids, endometriomas, or other pelvic findings.

4. Hormone Testing and Preoperative Assessment

Depending on your needs, tests may include FSH, LH, estradiol (E2), prolactin, thyroid function, blood counts, and coagulation tests. Assessment for anesthesia and egg retrieval is also arranged.

5. Infectious Disease Screening

Relevant screening is usually required before treatment to support safe laboratory handling and storage.

How Does an Egg Freezing Cycle Work?

Egg freezing treatment pathway

Step 1: Begin Ovarian Stimulation

Treatment usually begins around the start of a menstrual cycle. Your doctor selects a personalized medication protocol based on AMH, AFC, age, body weight, and any previous response to treatment.

Stimulation takes approximately 11 to 14 days, although the actual duration and medication dose depend on your ovarian response and your doctor’s assessment.

Step 2: Monitor Follicle Growth

Follow-up visits include transvaginal ultrasound and blood tests to assess follicle size, follicle number, and hormone changes.

Medication doses are adjusted as needed to support follicle growth and reduce the risks of premature ovulation or an excessive ovarian response.

Step 3: Receive the Trigger Injection

Once the follicles have reached an appropriate stage, a trigger injection is scheduled to support final egg maturation.

The timing is important. Egg retrieval is usually arranged approximately 34 to 36 hours after the injection.

Step 4: Egg Retrieval

The procedure is usually performed under anesthesia or sedation. Using transvaginal ultrasound guidance, the doctor collects follicular fluid with a retrieval needle. The embryology laboratory then identifies and assesses the eggs.

The number of eggs retrieved is not necessarily the same as the number of mature eggs, and not every follicle contains a retrievable egg.

Step 5: Freeze Mature Eggs

An embryologist assesses egg maturity. Suitable mature eggs are treated with cryoprotectant, rapidly cooled using vitrification, and stored in liquid nitrogen storage systems.

How Many Eggs Should Be Stored?

Illustration accompanying information on egg freezing

There is no single number that is right for everyone.

The target number of mature eggs depends on:

  1. Age at freezing
  2. The number of children you hope to have
  3. Egg survival after warming
  4. Fertilization and embryo development
  5. Sperm quality
  6. Future uterine health and overall health

As age increases, more mature eggs are generally needed to achieve a comparable chance of having a child. If the first cycle yields relatively few mature eggs, your doctor may discuss another cycle according to your needs. Multiple retrievals are not necessary for everyone.

What Symptoms May Occur After Egg Retrieval?

Mild bloating, lower abdominal discomfort, light vaginal spotting, nausea, fatigue, or dizziness after anesthesia may occur. Most symptoms gradually improve, although recovery varies.

Do not drive, ride a scooter or motorcycle, or operate machinery on the day of retrieval. Arrange for someone to accompany you home and follow the medical team’s instructions on rest and medication.

Contact the medical team promptly if you experience:

  1. Significantly worsening abdominal pain or bloating
  2. Difficulty breathing or chest tightness
  3. Persistent nausea or vomiting
  4. Markedly reduced urine output
  5. Rapid weight gain over a short period
  6. Heavy vaginal bleeding
  7. Fever, chills, or dizziness

These symptoms may be associated with OHSS, bleeding, or infection and require medical assessment.

What Are the Risks and Limitations of Egg Freezing?

Ovarian Hyperstimulation Syndrome (OHSS)

Some patients with a strong response to stimulation may develop enlarged ovaries, bloating, abdominal fluid accumulation, or other symptoms. Your doctor adjusts medication according to AMH, AFC, and your response during treatment to reduce the risk of moderate or severe OHSS.

Uncertainty About Future Outcomes

Future outcomes also depend on egg survival after warming, fertilization, embryo development, sperm quality, uterine health, and overall health. The number of children you hope to have also affects how many eggs may be needed. Egg freezing cannot guarantee a future pregnancy or live birth.

Egg Freezing: Frequently Asked Questions

Can I safely delay pregnancy indefinitely after freezing my eggs?

No. Egg freezing may provide more options, but it does not remove the risks of pregnancy at an older age or guarantee that enough eggs will develop into usable embryos.

Can I freeze my eggs if my AMH is low?

A low AMH does not automatically rule out treatment, but fewer eggs may be obtained after stimulation. Your doctor considers age, AFC, menstrual patterns, and medical conditions when planning treatment.

Can I freeze my eggs if my periods are irregular?

An assessment is the first step. Irregular periods may be associated with ovulatory disorders, polycystic ovary syndrome, thyroid conditions, or other hormonal issues. The cause should be evaluated before selecting a suitable treatment plan.

Does egg freezing make me run out of eggs sooner?

Ovarian stimulation mainly supports the growth of follicles that would otherwise undergo natural degeneration during that cycle. It does not retrieve all of your future eggs in advance. Treatment is still individualized according to ovarian function and medical assessment.

Preserving Options Starts with Understanding Your Fertility

The decision to freeze eggs should not be based on age or a single AMH value alone. A comprehensive assessment helps clarify your ovarian reserve, the likely number of mature eggs obtainable, and what egg freezing may mean for your plans.

The Reproductive Medicine Center at Sung Jun Hung Women’s and Children’s Hospital provides fertility assessments, egg freezing, laboratory cryopreservation, and future reproductive planning, with professional support throughout your care.

Sperm freezing

Sperm Cryopreservation

Your Guide to Sperm Freezing

Who May Benefit, Testing, Storage, and Future Use

Fertility preservation is relevant to men as well as women. Sperm count and quality may be affected by illness, treatment, surgery, age, and reproductive health conditions. If you are preparing for treatment that may impair sperm production, or anticipate difficulty providing a semen sample in the future, consider discussing sperm freezing before treatment or surgery.

Sperm freezing is a relatively quick preservation option. It usually does not require prolonged medication or waiting for a particular biological cycle. However, a medical assessment and semen analysis are still needed, and sperm quality may change after freezing and thawing.

What Is Sperm Freezing?

Sperm freezing involves semen analysis and laboratory processing, followed by the addition of cryoprotectant. The sample is divided into storage units and preserved in liquid nitrogen storage systems.

Only the units needed for a treatment cycle are thawed, so the entire stored sample does not have to be used at once. Whether thawed sperm is suitable for IUI, IVF, or ICSI depends on sperm concentration, motility, survival after thawing, and the partner’s reproductive health.

Who May Consider Sperm Freezing?

Men Preparing for Cancer or Other Medical Treatment

Chemotherapy, pelvic radiation, some hormonal treatments, and surgery involving the testes or reproductive system may affect sperm production. If the schedule allows, sperm freezing should be completed before treatment that may damage reproductive cells. The American Society for Reproductive Medicine (ASRM) recommends preserving sperm before cancer treatment whenever possible.

Men with Reduced Sperm Count or Motility

If semen analysis shows a low sperm count, reduced motility, or substantial variation in sample quality, your doctor may recommend storing sperm in advance in case sufficient sperm cannot be obtained on the treatment day.

Men with Collection Difficulties or Anticipated Ejaculatory Problems

Men with spinal cord injuries, neurological conditions, ejaculatory disorders, or planned surgery that may affect ejaculation can discuss preservation in advance.

Men Who Require Surgical Sperm Retrieval

For some men with obstructive or non-obstructive azoospermia, sperm can be retrieved from the epididymis or testes. Unused sperm may be frozen to reduce the need for repeat retrieval procedures.

Men with Occupational Risks or Specific Reproductive Plans

If work may involve exposure to heat, radiation, or chemicals, or if frequent travel, military service, or other commitments may affect future treatment arrangements, semen analysis can help guide a discussion about preservation needs.

How Should I Prepare for Sperm Freezing?

  1. Medical consultation: Your doctor reviews medical, surgical, and reproductive history, medications, occupational exposures, lifestyle, and reproductive plans. If preservation is needed before medical treatment, provide the diagnosis, treatment details, and planned start date so the teams can coordinate arrangements.
  2. Abstinence period: Our center asks patients to abstain from ejaculation for three to five days before a full semen analysis. A shorter or longer interval may affect semen volume, sperm concentration, and motility. Tell the laboratory your actual abstinence period when providing the sample.
  3. Medication and health review: Inform your doctor about recent fever or infection and any hormones, anabolic steroids, or other medications that may affect sperm production.

The Sperm Freezing Process

Step 1: Semen Collection

Our hospital provides a private collection room. The complete semen sample is collected by masturbation into a sterile container.

Do not use ordinary condoms or lubricants that have not been approved by the laboratory, as their ingredients may harm sperm. If any part of the sample is lost, tell the laboratory staff so the results can be interpreted appropriately.

Step 2: Semen Analysis

The laboratory assesses liquefaction, semen volume, sperm concentration, total sperm count, motility, vitality, and morphology.

A single result may be affected by abstinence duration, fever, illness, stress, sleep, and completeness of collection. If results are abnormal, your doctor may recommend repeat testing or referral to a specialist in male reproductive urology.

Step 3: Sample Processing

The embryology laboratory processes the sample according to its quality and adds cryoprotectant to help reduce damage from ice crystals and temperature changes during freezing.

Step 4: Division into Storage Units and Freezing

The sample is usually divided into several units, cooled according to laboratory protocols, and stored in liquid nitrogen storage systems.

Dividing the sample allows only the required units to be thawed for treatment, rather than using the entire stored sample at once.

Step 5: Confirm Storage Details

The hospital records the number of units stored, sample quality, storage date, and relevant consent documents. Keep your contact details up to date and complete storage renewals, payments, and other required procedures when notified.

How Many Samples or Storage Units Are Needed?

There is no single standard. Recommendations depend on:

  1. Initial sperm concentration and motility
  2. The estimated number of usable sperm after thawing
  3. The assisted reproductive treatment likely to be used
  4. Whether irreversible treatment or surgery is planned
  5. Whether there is time for multiple collections
  6. The partner’s age and reproductive health

If treatment has not yet started and time allows, multiple collections may increase the amount available for future use. If treatment is urgent, discuss preservation promptly even if only one sample can be collected.

Can Freezing Damage Sperm?

Some sperm may lose motility or fail to survive freezing and thawing. The number of viable, motile sperm after thawing may therefore be lower than before freezing.

However, frozen sperm has long been used in assisted reproduction. Pregnancy outcomes depend not only on whether sperm is frozen, but also on post-thaw quality, the treatment method, egg quality, and both partners’ reproductive health.

How Can Frozen Sperm Be Used?

Intrauterine Insemination (IUI)

IUI may be considered if enough motile sperm remain after thawing and the partner’s ovulation and fallopian tube function are suitable.

In Vitro Fertilization (IVF)

Retrieved eggs are fertilized with prepared sperm in the laboratory and then cultured into embryos.

Intracytoplasmic Sperm Injection (ICSI)

If sperm count or motility is low, or sperm was obtained surgically, an embryologist may inject a single sperm into an egg to assist fertilization.

What Are the Limitations of Sperm Freezing?

Not all sperm survive thawing: Tolerance to freezing varies between individuals, and some samples show reduced motility after thawing.

Future parenthood is not guaranteed: Embryo development and live birth also depend on egg quality, uterine conditions, embryo factors, and both partners’ overall health.

Storage and use must meet applicable requirements: Storage, renewal, disposal, and future use of reproductive cells are subject to Taiwan’s assisted reproduction laws, signed consent documents, and institutional policies.

Sperm Freezing: Frequently Asked Questions

Does sperm freezing require hospitalization?

Routine semen collection and freezing generally do not require hospitalization. If anesthesia or surgical sperm retrieval is needed, arrangements depend on the procedure and the hospital’s guidance.

Can a cold or fever affect sperm?

Fever and acute illness may temporarily affect semen quality. Tell your doctor about recent high fever, serious infection, or relevant medications so they can decide whether to collect a sample immediately or arrange follow-up.

Do I need sperm freezing if my semen analysis is normal?

Not necessarily. If you have no planned treatment, surgery, or other specific risk to fertility, freezing may not be needed. The decision should consider medical conditions, reproductive plans, and semen quality.

Can I still conceive naturally after freezing sperm?

Sperm freezing itself does not impair sperm production. The ability to conceive naturally depends on subsequent health, the effects of medical treatment, and both partners’ reproductive factors.

Men Have an Important Role in Early Fertility Planning

If an illness or treatment may affect sperm production, discuss fertility preservation before treatment rather than waiting until it is completed. Earlier referral often provides more opportunity to arrange suitable preservation without delaying essential medical care.

The Reproductive Medicine Center at Sung Jun Hung Women’s and Children’s Hospital provides male fertility assessments, semen analysis, sperm freezing, and assisted reproduction consultations to help preserve options for your future family plans.

AMH testing and ovarian reserve assessment

Ovarian Reserve Assessment

AMH Testing & Ovarian Reserve Assessment

Understanding AMH Levels and What They Mean

“Is my AMH normal?” “Does a low AMH mean I cannot get pregnant?” “Does a higher AMH mean better fertility?”

AMH is a blood test commonly used in fertility assessment. It helps estimate ovarian reserve and predict the response to ovarian stimulation. However, it is not a test of egg quality, a prediction of natural pregnancy, or a guarantee of future parenthood.

AMH should not be interpreted as a single number in isolation. Age, menstrual patterns, AFC, medical and surgical history, and current reproductive plans all matter.

What Is AMH?

AMH stands for anti-Müllerian hormone.

In adult women, it is produced mainly by small growing follicles in the ovaries. As the number of these follicles generally decreases with age, AMH can serve as a marker of ovarian reserve.

What Can AMH Tell Us?

An Estimate of Ovarian Reserve

AMH broadly reflects the number of small follicles available for recruitment in the ovaries.

The Likely Response to Ovarian Stimulation

Before egg freezing or IVF, AMH helps estimate how the ovaries may respond to medication and how many eggs may be obtained. A lower AMH may be associated with fewer eggs, while a higher AMH may indicate a stronger response requiring dose adjustment and monitoring for OHSS.

Support for Personalized Treatment Planning

Your doctor considers AMH together with AFC, age, and body weight when selecting a stimulation protocol and medication dose.

What Can AMH Not Tell Us?

It Does Not Directly Measure Egg Quality

Ovarian reserve refers to egg quantity. Egg quality relates to the potential of an egg to develop into a viable embryo and result in a live birth. These are different concepts. Age remains an important factor in assessing egg quality and the likelihood of chromosomally normal embryos.

It Cannot Independently Predict Natural Pregnancy

A low AMH does not mean natural conception is impossible, and a normal or high AMH does not guarantee easy conception. Ovarian reserve testing is more useful for predicting egg yield after stimulation than for predicting natural conception on its own.

It Does Not Assess Every Factor Involved in Fertility

Pregnancy also depends on ovulation, fallopian tube function, the uterine cavity, sperm quality, and embryo development. A fertility assessment therefore usually involves both partners, rather than testing only the woman’s AMH.

How Is AMH Tested?

AMH is measured with a blood test and does not require surgery.

AMH usually varies less across the menstrual cycle than some other reproductive hormones, so testing is generally not restricted to cycle day two or three. If FSH, LH, or E2 are being measured at the same time, your doctor may still schedule testing early in the cycle to support interpretation.

Hormonal contraceptives may temporarily affect AMH levels. Tell your doctor about any contraceptives, hormonal medication, or other treatments before testing. Do not stop prescribed medication on your own.

Who May Consider AMH Testing?

Women Who Are Not Yet Planning Pregnancy but Want to Understand Ovarian Reserve

AMH testing and ultrasound may be discussed as part of an assessment to support future reproductive planning.

Women Considering Egg Freezing

AMH helps estimate the likely egg yield after stimulation and is one of the factors considered before an egg freezing cycle.

Couples Who Have Been Trying to Conceive Without Success

A comprehensive fertility assessment is generally recommended after 12 months of regular unprotected intercourse for women under 35, or after six months for women aged 35 or older. Earlier assessment may be appropriate if there are irregular periods, ovarian conditions, or other risk factors.

Women with a History of Ovarian Surgery

Surgery for ovarian cysts, endometriomas, or other ovarian conditions may affect ovarian tissue and reserve. Your doctor can assess whether AMH testing before or after surgery would be useful.

Women with Changes in Menstrual Patterns or a Family History of Early Menopause

If cycles become shorter or irregular, or a mother or sister experienced early menopause, discuss whether further assessment is appropriate.

Women Preparing for Cancer Treatment or Other Treatment That May Affect the Ovaries

Seek an early fertility preservation assessment before chemotherapy, radiation therapy, or relevant ovarian surgery whenever possible.

How Are AMH Levels Interpreted?

There is no single normal AMH value that applies to every age, testing method, and clinical situation.

Reference ranges vary between laboratories, testing platforms, and age groups. Avoid interpreting your result using a fixed value found online without clinical context.

AMH Below the Expected Range for Your Age

This may indicate fewer recruitable follicles and a lower egg yield during egg freezing or IVF.

However, a low result does not necessarily mean there are no eggs, ovulation has stopped, or natural pregnancy is impossible. Age, menstrual patterns, and ultrasound findings must also be considered.

AMH Within the Expected Range for Your Age

This suggests ovarian reserve is broadly consistent with age. It does not guarantee normal egg quality or exclude tubal, uterine, ovulatory, or male fertility factors.

AMH Above the Expected Range for Your Age

A higher AMH usually reflects a greater number of small follicles, but it does not necessarily mean a higher chance of pregnancy.

Patients with higher AMH and AFC may respond more strongly to stimulation and require attention to OHSS risk. Whether the finding is related to polycystic ovary syndrome must be assessed alongside menstrual patterns, hormone findings, and ultrasound results.

Does AMH Decline with Age?

In general, the number of ovarian follicles decreases with age, and AMH usually follows a declining trend.

However, ovarian reserve and the rate of decline vary between individuals. Women of the same age may have substantially different AMH levels. Age and AMH should therefore be considered together.

What Should I Do If My AMH Is Low?

The first step is to check whether the result is consistent with your age, ultrasound findings, and other test results, rather than starting supplements on your own.

Your doctor may assess:

  • Menstrual patterns and ovulation
  • Antral follicle count
  • FSH and estradiol (E2)
  • A history of ovarian surgery or disease
  • Current hormonal medications
  • Near-term reproductive plans
  • Whether egg freezing or assisted reproduction should be considered

There is currently no treatment that can replenish eggs already lost from the ovarian reserve. Planning focuses on choosing an appropriate approach based on existing ovarian function and your reproductive timeline.

Does a High AMH Need Treatment?

A high AMH is not a disease in itself and does not necessarily require treatment.

If it occurs with infrequent or irregular periods, prolonged lack of ovulation, signs of androgen excess, or a high number of small follicles on ultrasound, your doctor may assess for polycystic ovary syndrome or another ovulatory condition.

If egg freezing or IVF is planned, medication and monitoring are adjusted according to the risk of an excessive ovarian response.

Should AMH Be Monitored Regularly?

The need for repeat testing depends on age, the initial result, medical history, and reproductive plans.

Frequent testing is not necessarily needed if there are no specific risks and pregnancy is planned soon. Your doctor may recommend follow-up if AMH is lower than expected for age, you have had ovarian surgery, you plan to delay pregnancy, or you are facing treatment that may affect ovarian function.

When monitoring changes, using the same laboratory or a comparable testing method can help reduce variation between testing systems.

What Else Is Included in a Comprehensive Fertility Assessment?

Transvaginal Ultrasound and AFC

Ultrasound assesses small follicles in both ovaries and examines the ovaries, uterus, and pelvis. Both AMH and AFC are commonly used to assess ovarian reserve.

FSH and Estradiol (E2)

These are usually measured early in the menstrual cycle. FSH can vary between cycles, so ovarian function should not be judged from one result alone.

Ovulation and Fallopian Tube Assessment

If you are trying to conceive or undergoing an infertility assessment, your history may indicate a need to assess ovulation and whether the fallopian tubes are open.

Semen Analysis

Male factors may affect conception independently or together with female factors. A comprehensive assessment should include semen analysis.

AMH: Frequently Asked Questions

Does a low AMH mean premature ovarian insufficiency?

Not necessarily. Premature ovarian insufficiency cannot be diagnosed from AMH alone. Menstrual patterns, FSH, E2, and clinical findings must also be considered.

Does a normal AMH mean there are no fertility concerns?

No. It suggests ovarian reserve is broadly within the expected range, but it does not confirm normal egg quality, fallopian tube function, uterine conditions, or sperm quality.

Can I conceive naturally with a low AMH?

It may still be possible if ovulation continues and sperm and fallopian tube factors are suitable. AMH has limited ability to predict natural conception on its own.

Does a low AMH mean I must freeze my eggs?

Not necessarily. The decision depends on age, near-term pregnancy plans, AFC, likely egg yield, and future family plans. If you are ready to have children now, your doctor may recommend trying to conceive or completing an infertility assessment rather than focusing only on egg freezing.

Can supplements increase AMH?

AMH results may vary because of testing differences and some physiological or medication-related factors. A supplement should not be regarded as a way to increase the egg supply. Discuss any supplements with your doctor to avoid interference with existing conditions or treatment.

AMH Is a Planning Tool, Not a Fertility Score

The purpose of AMH testing is not to decide whether someone “can or cannot have children” based on a single number. It helps clarify ovarian reserve and supports timely planning for pregnancy, egg freezing, or assisted reproduction.

The Reproductive Medicine Center at Sung Jun Hung Women’s and Children’s Hospital provides AMH testing, transvaginal ultrasound, AFC assessment, male and female fertility assessments, and personalized consultations to support informed reproductive decisions.

CONSULTATION

Consultation Form

Every fertility journey deserves attentive care. Please leave your needs and contact information, and our team will help you explore the treatment options that may be right for you.

*Required field

If you need any assistance, please contact us. We will get back to you as soon as possible.

Can’t read it? Click the image to refresh.

Submit

